HIPAA security awareness training
45 CFR §164.308(a)(5) names security awareness and training as an Administrative Safeguard, with four implementation specifications that OCR asks about one by one.
Five-to-ten-minute 3D exercises mapped to each HIPAA duty, with completion evidence your auditor can export.
At a glance
- Who
- Covered entities and, since 2013, their business associates
- Standards
- §164.308(a)(5) security and §164.530(b) privacy training
- Annual cap
- About $2.1M per violation category, adjusted for inflation
- Retention
- Six years under §164.316(b)(2)
Trusted by teams at












Founded by the creator of Kontra Application Security Training.
Play the exercises behind your HIPAA program
Each one is a 3D scenario your staff finish in 5 to 10 minutes. Pick one and play it here, with no sign-up.
Exercises run in interactive 3D environments.
Four specifications, each a question OCR asks
All four are addressable: implement it, implement an equivalent, or document in writing why neither is reasonable.
- (ii)(A) Security reminders Ongoing nudges through the year, not one annual video.
- (ii)(B) Protection from malicious software Spotting phishing and reporting malware before it spreads.
- (ii)(C) Log-in monitoring Noticing odd sign-in activity and reporting it.
- (ii)(D) Password management Creating, changing and safeguarding credentials.
The Privacy Rule duty at §164.530(b) has no addressable route: training is required outright.
§164.308 and §164.530, mapped to exercises
Each implementation specification, matched to scenarios clinicians, billing teams and IT actually face.
§164.308(a)(5) Security Awareness §164.530(b) Privacy Training §164.308(a)(6) Incident Procedures §164.312(d) Authentication §164.310(b) Workstation Security §164.308(a)(3) Workforce Security §164.308(a)(1)(ii)(B) Risk Analysis (AI Tools) §164.312(a)(1) Access Control (Cloud & Repositories) Resolution Agreements where training was in the findings
Each one ended with a corrective action plan that named workforce training.
2018 Anthem $16M Resolution Agreement (78.8M records)
Anthem signed a $16 million Resolution Agreement with OCR in October 2018 over the 2014-2015 attack that exposed electronic PHI for 78.8 million people. It started with a spear phishing email opened by an employee at an Anthem subsidiary, which gave attackers lasting access to the data warehouse.
OCR found Anthem had not done an enterprise-wide risk analysis, did not review system activity regularly, failed to spot and respond to suspected incidents, and lacked adequate minimum access controls.
It was the largest HIPAA settlement on record at the time. A multi-year corrective action plan followed, covering risk analysis, access management, training and OCR monitoring.
2023 Banner Health $1.25M settlement (2.81M records)
Banner Health, based in Phoenix, agreed in February 2023 to pay $1.25 million and follow a corrective action plan after a 2016 attack that affected 2.81 million people. Attackers got into a server running payment applications and moved into systems holding PHI for patients, health plan members and providers.
OCR cited missing or inaccurate risk analysis, no monitoring of system activity, weak authentication, and missing technical safeguards.
The two-year plan required a new risk analysis, updated policies and procedures, and new workforce training.
2022 Lafourche Medical Group $480K settlement
Lafourche Medical Group, a Louisiana primary care practice, agreed in December 2022 to pay $480,000 after a 2021 phishing attack exposed PHI for about 34,862 people.
OCR found no Security Rule risk analysis before the breach and no procedures for reviewing audit logs or other system activity.
The case gets cited because the practice was small, yet OCR still settled for six figures with a plan requiring risk analysis, written policies and training. OCR Director Melanie Fontes Rainer said phishing is the most common way hackers get into healthcare systems and that organisations of every size must take steps, including training.
Workforce training for §164.308(a)(5)
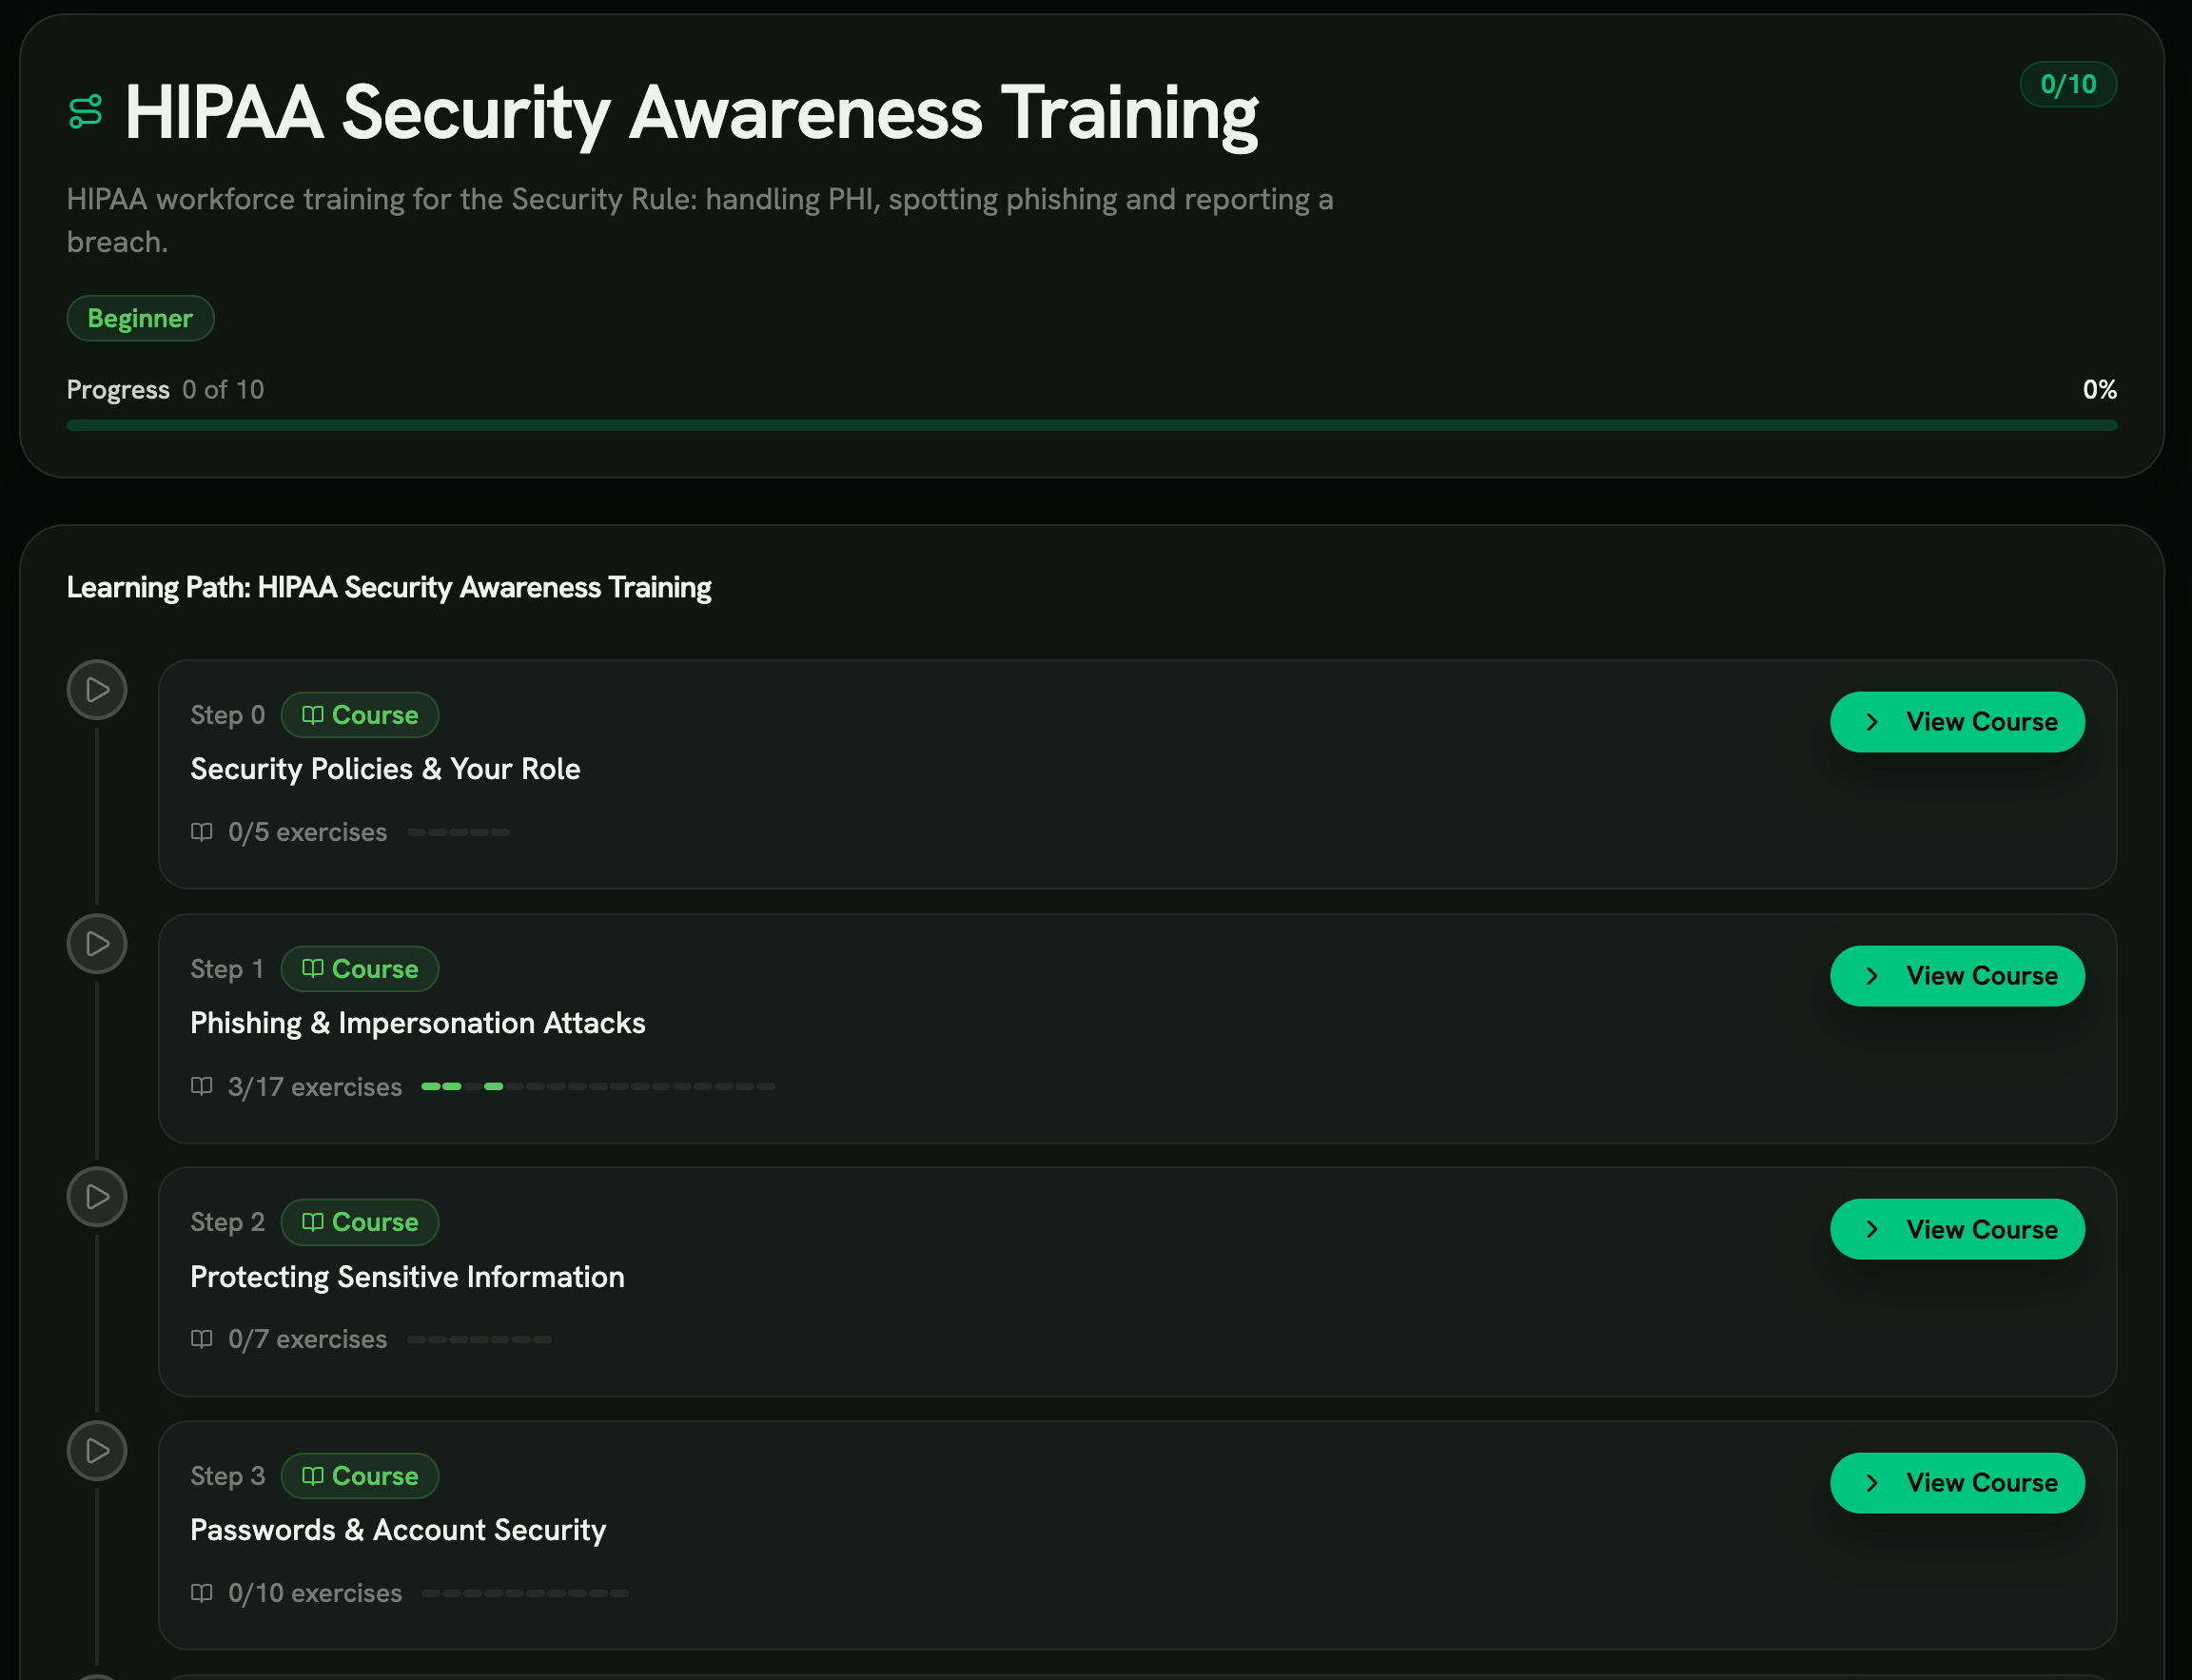
The HIPAA path covers what the Security Rule names: PHI handling, access, breach reporting and workstation safeguards.
- Ten steps
- From security policies and your role to device and workstation security.
- PHI at the centre
- Protecting sensitive information comes early, before passwords and access.
- Per workforce member
- Each person’s progress is kept for the six-year §164.316 retention period.
The specifications, the Privacy Rule duty and BA flow-down
Scope, the four specifications, Privacy Rule training and business associate flow-down.
01 Scope: workforce members, business associates, and what counts as PHI
The Security Rule covers electronic PHI at every covered entity and business associate. 45 CFR §160.103 defines the workforce broadly: employees, volunteers, trainees and anyone else whose conduct the entity directly controls, paid or not.
PHI means health information tied to any of the 18 identifiers in the Privacy Rule, such as names, dates, MRNs, biometrics and full-face photos.
Anyone who can see, send, store or change PHI at work is in scope for §164.308(a)(5) training. That includes agency nurses, IT contractors, EHR vendors, billing services, cloud platforms and revenue cycle vendors.
02 §164.308(a)(5): the four implementation specifications
§164.308(a)(5) names four implementation specifications:
- Security reminders: ongoing communication such as monthly threat notes, posters, phishing microlearning and policy refreshers, not one annual event.
- Protection from malicious software: how to guard against, detect and report malware. Phishing and ransomware training belongs here, since phishing is still the main way malware reaches hospitals.
- Log-in monitoring: watching access attempts and reporting anything odd, including failed log-ins on your own account.
- Password management: creating, changing and protecting credentials. Current programs add password managers, MFA setup and the risk of reused passwords.
03 §164.530(b): the Privacy Rule training duty
The Privacy Rule’s training duty at §164.530(b) is required, not addressable, and sits alongside the Security Rule.
It covers privacy policies and procedures: the minimum necessary standard, permitted uses and disclosures, patient rights to access, amendment and an accounting of disclosures, the Notice of Privacy Practices, and the §164.508 authorization process.
Staff must be retrained within a reasonable time after a material policy change. In practice that means whenever the Notice of Privacy Practices changes or a new patient-facing process goes live.
04 Per-workforce-member documentation auditors expect
§164.316(b)(2)(i) of the Security Rule and §164.530(j) of the Privacy Rule require you to keep documentation for six years from creation or from when it was last in effect, whichever is later. Training records are included.
In an investigation, OCR typically asks for each workforce member’s name and role, completion date, the content delivered with its version, assessment results, signed acknowledgments where policy requires them, and remediation records for anyone who failed.
A dashboard summary is handy, but OCR wants the underlying records.
05 Refresh cadence: new hire, periodic, and material-change triggers
New hires finish training before they touch PHI, not weeks after starting.
The Security Rule calls for periodic training without setting a frequency. Annual refreshers are the accepted baseline, and quarterly microlearning fits the security reminders specification better.
Retraining should also follow a policy update, an EHR change, or an incident that exposed a gap. The same applies when someone takes on new PHI duties, such as a nurse moving to billing or a developer getting production EHR access.
06 BA flow-down through the Business Associate Agreement
§164.308(b) and §164.504(e) require a Business Associate Agreement with every BA that creates, receives, maintains or transmits PHI. Since the 2013 Omnibus Rule, BAs are directly liable for Security Rule duties, training included.
The BAA should state the training expected, how often, and the §164.410 timeline for reporting incidents back to the covered entity.
Mature vendor programs now ask for proof of BA training during due diligence, and many require a yearly attestation.
07 Ready for the OCR sample request
HIPAA training works when it feels like a shift. Each exercise puts the learner in a simulated EHR session, phone call, inbox or workstation handover and asks for a decision.
Every scenario maps to at least one §164.308(a)(5) specification. Feedback names the cue that was missed, the policy that applies, and the check that would have stopped a real attack.
Scenarios stick better than video for the same time, which matters when OCR asks whether training changed behaviour or only produced certificates.
A nurse and a coder handle PHI differently, so assignments follow the role:
- Clinicians: scenarios from real ED and inpatient incidents, such as fake medical suppliers during EHR migrations, fake patient portal resets and social engineering at nursing stations.
- Billing, coding and revenue cycle: minimum necessary, redaction, fax handling, and BEC aimed at AP.
- IT and help desk: vishing, MFA-reset pretexts and the social engineering used by Scattered Spider in 2023.
- Executives and BAs: whaling, deepfake video and securing phones that carry work email.
The evidence pack answers an OCR sample request. Each record holds the person’s name and role, completion date, content and version, assessment result, and signed acknowledgment where policy requires one.
Records are kept for the six years required by §164.530(j) and §164.316(b)(2)(i).
Refreshers go out automatically after material policy changes, when roles change, and every quarter for security reminders. OCR gets the records it asks for, not a summary chart.
Each safeguard, matched to the scenario that trains it
Safeguards OCR tends to cite in the same paragraph.
§164.308(a)(5)(ii)(A): Security reminders
Security reminders are meant to be ongoing. RansomLeak sends monthly scenarios on current threats and short refreshers that take five to ten minutes each.
Every cycle leaves a dated record with the content version, kept for the six-year retention period OCR asks about.
§164.308(a)(5)(ii)(B): Protection from malicious software
For protection from malicious software, the phishing exercise practises checking AI-written lures, the ransomware exercise covers recognise, isolate and report, and the safe GenAI exercise covers prompt injection through AI assistants.
Each one ends with the reporting route your organisation actually uses, so the habit carries over to a real incident.
§164.308(a)(5)(ii)(C): Log-in monitoring
Log-in monitoring asks staff to notice and report odd account activity. The MFA fatigue exercise covers the push-spamming used in the 2022 Uber breach. The encryption and lock discipline exercise covers shared workstations and unattended sessions in clinical and billing areas.
Both end with the reporting steps, including the §164.308(a)(6) incident path.
§164.308(a)(5)(ii)(D): Password management
For password management, the MFA setup exercise covers password managers, enrolment, and moving high-risk roles from SMS and TOTP to phishing-resistant FIDO2 keys.
The encryption and lock discipline exercise covers how credentials leak in practice: unlocked workstations, shared logins at nursing stations, and shift handovers.
§164.530(b): Privacy Rule training
For the Privacy Rule, three exercises cover the policies staff must know. PII document redaction puts minimum necessary into practice, data classification basics covers spotting and handling PHI, and identity theft prevention shows what exposure does to patients.
When you record a material policy change, refresher assignments go out automatically.
§164.308(a)(6): Security incident procedures
The incident procedures standard covers spotting, responding to and reporting incidents. The incident reporting and security incident response exercises cover the warning signs, first containment steps, internal escalation, and the §164.410 timeline for business associates to notify the covered entity.
Their completion records line up with the corrective action plans OCR writes into Resolution Agreements.
§164.312(d): Person or entity authentication
§164.312(d) requires you to verify that a person seeking PHI access is who they claim to be.
The MFA setup exercise covers the technical control. The tech support scams exercise covers help desk social engineering that gets around authentication through password and MFA resets. The deepfake audio exercise covers voice cloning that defeats voice checks.
Together they cover the human side of a technical safeguard.
§164.310(b) and §164.308(a)(1)(ii)(B): Workstation security and risk analysis
Workstation security covers the physical side of devices that reach PHI. Mobile device security covers handhelds on the ward, encryption and lock discipline covers shared workstations, and joiner-mover-leaver awareness covers granting and removing access, which the §164.308(a)(1)(ii)(B) risk analysis often flags.
The accidental insider threat exercise completes the people side of the risk analysis.
Recommended exercises
Built around nursing stations, billing queues and EHR sign-ins.
- Phishing Practises §164.308(a)(5)(ii)(B) on malicious software. Phishing is the main ransomware route in healthcare and started the 2014-2015 Anthem breach. Try the exercise
- Ransomware Covers recognise, isolate and report for ransomware, the attack behind the largest HHS breach postings since 2020. Try the exercise
- MFA Setup & Best Practices Covers password management under §164.308(a)(5)(ii)(D) and authentication under §164.312(d), including moving high-risk clinical and IT roles from SMS to FIDO2. Try the exercise
- MFA Fatigue Attack Practises log-in monitoring under §164.308(a)(5)(ii)(C) with push-spamming like the 2022 Uber breach. Try the exercise
- Tech Support Scams Help desk social engineering that gets around §164.312(d) through password and MFA resets, as Scattered Spider did in 2023. Try the exercise
- PII Document Redaction Minimum necessary under the §164.530(b) Privacy Rule duty, with drills on records, fax and documents in billing and clinical work. Try the exercise
- Encryption & Lock Discipline Workstation security under §164.310(b) and the unattended sessions common at nursing stations, billing desks and shared clinical machines. Try the exercise
- Mobile Device Security Handheld PHI access on the ward under §164.310 and §164.312, including the personal-device exposure behind several six-figure OCR settlements with hospitals. Try the exercise
- Safe GenAI Usage Pasting clinical data into public AI tools is an unauthorised disclosure under the Privacy Rule. This exercise shows where the line is. Try the exercise
- General Incident Reporting The §164.308(a)(6) incident procedures: warning signs, internal escalation and the §164.410 notice timeline for business associates. Try the exercise
Further reading
Related glossary terms
References
- HIPAA Compliance and Enforcement HHS Office for Civil Rights
- 45 CFR Part 164: Security and Privacy Electronic Code of Federal Regulations
- NIST SP 800-66 Rev 2: Implementing the HIPAA Security Rule NIST
- HIPAA Security Rule Cybersecurity Guidance HHS Office for Civil Rights
- Cost of a Data Breach Report 2024 IBM
Answer an OCR data request in an afternoon
Role-based HIPAA scenarios and six years of per-person records.
Frequently asked questions
What is HIPAA security awareness training?
HIPAA security awareness training is the Administrative Safeguard at 45 CFR §164.308(a)(5) that every covered entity and business associate must run for every workforce member who touches protected health information. The HHS Office for Civil Rights routinely cites training gaps in seven and eight-figure Resolution Agreements, and the corrective action plans last for years.
What is HIPAA §164.308(a)(5)?
45 CFR §164.308(a)(5) is the Security Rule standard titled "Security Awareness and Training." It requires every covered entity and every business associate to "implement a security awareness and training program for all members of its workforce, including management."
The standard is supported by four implementation specifications: security reminders (§164.308(a)(5)(ii)(A)), protection from malicious software (§164.308(a)(5)(ii)(B)), log-in monitoring (§164.308(a)(5)(ii)(C)), and password management (§164.308(a)(5)(ii)(D)). All four are classified as addressable, but addressable does not mean optional. The entity must implement the specification, implement an equivalent alternative, or document in writing why the specification is not reasonable and appropriate.
Does HIPAA require security awareness training for all employees?
Yes. The Security Rule at §164.308(a)(5) requires training for all members of the workforce, including management. Workforce is defined broadly at 45 CFR §160.103 to include employees, volunteers, trainees, and any other persons whose conduct is under the direct control of the entity, paid or unpaid.
If a person can see, send, store, or change PHI in the course of their work, they are in scope. That includes agency nurses, IT contractors, EHR vendors, billing services, and revenue cycle vendors. Business associates are bound by the same training duty under §164.308 and through the Business Associate Agreement, with direct liability since the 2013 Omnibus Rule.
How often does HIPAA training need to be refreshed?
The Security Rule describes training as periodic without naming a frequency. Industry practice and OCR guidance converge on annual refresh as the accepted baseline for all workforce members, with quarterly microlearning increasingly used to satisfy the security reminders specification more cleanly.
Targeted training is also triggered by material policy changes (Privacy Rule duty under §164.530(b)), by role changes when workforce members take on new PHI-handling responsibilities, and after significant incidents that reveal a training gap. New hires must complete training before they access PHI, not weeks after they join.
What evidence do OCR investigators look for during a HIPAA training audit?
OCR sample requests routinely ask for the underlying records, not the summary dashboard view. The records that tend to survive scrutiny include workforce member name and role, date of completion, content delivered with version numbers, assessment results where applicable, signed acknowledgments where policy requires them, and remediation records for staff who failed assessments.
The Security Rule at §164.316(b)(2)(i) and the Privacy Rule at §164.530(j) require retention for six years from the date of creation or the date the record was last in effect, whichever is later. Training records explicitly fall in scope. Build the storage structure before the OCR letter arrives, because reconstructing six years of training history under audit pressure is where most entities lose the corrective action argument.
Do business associates need HIPAA training?
Yes. Business associates have been directly liable for Security Rule obligations, including workforce training, since the 2013 Omnibus Rule that implemented HITECH. The training duty at §164.308(a)(5) applies to BAs in the same way it applies to covered entities.
Mature vendor management programs ask for evidence of BA training as part of vendor due diligence and require an annual attestation. The Business Associate Agreement should specify the training expectation, the cadence, and the §164.410 incident notification timeline back to the covered entity. A BAA without these terms leaves the covered entity exposed when the BA suffers a breach.
What happens if HIPAA training is missing during an OCR investigation?
OCR penalty tiers are structured by culpability and inflation-adjusted annually. The 2024 figures set the minimum at roughly $137 per violation at the lowest tier and the maximum at $68,928 per violation at the highest, with an annual cap near $2,067,813 per identical-violation category. Willful neglect that is not corrected sits at the top of the schedule.
Beyond the per-violation fines, OCR Resolution Agreements bundle a civil monetary penalty with a multi-year corrective action plan that almost always includes revised training, third-party monitoring, and reporting back to OCR. State Attorneys General also have independent enforcement authority under HITECH. The Anthem ($16M, 2018), Banner Health ($1.25M, 2023), and Lafourche Medical Group ($480K, 2022) Resolution Agreements all carry training findings in the public text.
What is the difference between HIPAA Security Rule training and Privacy Rule training?
Security Rule training under §164.308(a)(5) covers the four implementation specifications: security reminders, protection from malicious software, log-in monitoring, and password management. The focus is on protecting electronic PHI from unauthorized access, alteration, or destruction. The four specifications are classified as addressable, though OCR rarely accepts a documented alternative at face value.
Privacy Rule training under §164.530(b) covers privacy policies and procedures: minimum necessary standard, permitted uses and disclosures, patient rights (access, amendment, accounting of disclosures), Notice of Privacy Practices, and the §164.508 authorization workflow. The Privacy Rule training duty is required (not addressable) and includes a refresh trigger within a reasonable time after material policy changes. Most mature programs run both in a single integrated curriculum so workforce members see the safeguards as one duty rather than two separate compliance boxes.
Are AI tools like ChatGPT a HIPAA risk?
Yes, when workforce members paste PHI into a public AI tool that lacks a Business Associate Agreement. PHI shared with a third-party large language model is a disclosure under the Privacy Rule and an unauthorized transmission under the Security Rule. Most public AI products do not sign BAAs, and even those that offer enterprise tiers with BAAs require careful configuration to remain compliant.
The risk surface includes copy-pasting clinical notes for summarization, sharing patient data for differential diagnosis suggestions, and uploading PHI documents for transcription or translation. Workforce training should cover safe GenAI usage with concrete examples of what counts as PHI, what an enterprise BAA-covered tier looks like, and the entity's approved-tools policy. The safe GenAI usage and sensitive data exposure through AI exercises in the catalogue cover this directly.